What Is Srs Surgery Explained Clearly For Transgender Patients
Sex Reassignment Surgery remains one of the most transformative yet misunderstood procedures in modern medicine despite its critical role in gender-affirming care. For transgender individuals, this surgery is not merely a medical intervention but a lifeline toward aligning physical identity with deeply held self-perception. Historical barriers, from early 20th-century stigma to today’s evolving ethical debates, have shaped its development, reflecting broader societal struggles over gender recognition and human rights.
Globally, demand for gender-affirming surgeries has surged as medical science advances and legal protections expand. According to the World Professional Association for Transgender Health (WPATH), over 100,000 transgender adults in the U.S. alone have undergone some form of gender-affirming surgery, with procedures now spanning from genital reconstruction to facial feminization. Yet misconceptions persist—whether about eligibility, recovery, or psychological preparedness—leaving many questioning what SRS truly entails beyond the headlines.
Understanding Sex Reassignment Surgery: Core Concepts and Definitions
Sex Reassignment Surgery (SRS), now more commonly referred to as gender-affirming surgery (GAS), represents a critical component of gender-affirming care for transgender and gender-diverse individuals. This medical intervention aligns a person’s physical characteristics with their gender identity, addressing dysphoria—a distress often experienced when one’s assigned sex at birth does not match their internal sense of self. Beyond physical transformation, SRS plays a pivotal role in mental health outcomes, reducing rates of depression, anxiety, and suicide among transgender individuals. The evolution of SRS reflects broader societal progress in recognizing gender diversity, alongside advancements in medical science that have made these procedures safer and more accessible. However, its definition, terminology, and ethical implications remain subjects of ongoing debate, shaped by cultural, legal, and medical perspectives. The historical and contemporary significance of SRS cannot be overstated. From early 20th-century experiments to today’s evidence-based, patient-centered approaches, the journey of SRS mirrors broader struggles for transgender rights and medical acceptance. Understanding its core concepts—including its medical, psychological, and social dimensions—is essential for demystifying the procedure and advocating for informed, compassionate care.
Medical and Non-Medical Definitions of SRS
 In medical contexts, SRS refers to surgical procedures that modify primary or secondary sexual characteristics to align with an individual’s gender identity. These interventions are part of a comprehensive care plan that may include hormonal therapy, mental health support, and social transitioning. The World Professional Association for Transgender Health (WPATH), a leading authority in transgender healthcare, defines SRS as a "medically necessary treatment for gender dysphoria" when diagnosed by a qualified professional. The term emphasizes the therapeutic intent of the surgery, aiming to reduce distress and improve quality of life.
Non-medically, SRS is often discussed in activist, legal, and cultural spheres as a symbol of self-determination and bodily autonomy. For many transgender individuals, the procedure is not merely a cosmetic change but a lifesaving intervention that restores a sense of wholeness. Misconceptions, however, persist—such as framing SRS as irreversible or frivolous—which underscores the need for accurate, stigma-free education. The shift from "sex reassignment" to "gender-affirming" reflects a broader movement toward patient-centered language, prioritizing the individual’s self-identified gender over binary medical classifications.
Historical Evolution of SRS: Milestones and Societal Shifts
The history of SRS is marked by medical experimentation, activism, and gradual normalization. Early attempts at gender-affirming surgeries date back to the 1930s, when German sexologist Magnus Hirschfeld pioneered techniques for transgender individuals, though these were largely unregulated and often dangerous. The 1950s and 1960s saw the first documented cases of vaginoplasty and phalloplasty, performed by surgeons like George J. Burou (Brazil) and Harold Gillies (New Zealand), who developed early methods for genital reconstruction. However, these procedures were experimental and carried high risks, with limited access for patients. The 1970s and 1980s brought institutionalization of SRS through programs like the Johns Hopkins Gender Identity Clinic (1966), which established diagnostic and surgical protocols. This era also saw the rise of transgender rights activism, with figures like Colette Grogan (a British transgender woman) and Lou Sullivan (an American journalist) advocating for medical recognition. By the 1990s, the Harry Benjamin International Gender Dysphoria Association (HBIGDA), a precursor to WPATH, formalized standards of care, requiring mental health evaluations and real-life experience (RLE) before surgery. The 21st century has witnessed depathologization efforts, with WPATH’s 7th Standards of Care (2017) emphasizing informed consent models over rigid diagnostic criteria. Countries like Argentina (2012) and Malta (2015) have legalized gender self-ID, removing surgical requirements for legal recognition. Meanwhile, medical advancements—such as improved phalloplasty techniques, vaginoplasty refinements, and facial feminization surgery (FFS)—have enhanced outcomes. However, disparities persist: low-income countries often lack access to specialized care, and transgender individuals of color face higher barriers due to systemic discrimination.
Terminology Comparison: SRS, GAS, GCS, and FFS
 The language used to describe gender-affirming surgeries has evolved to reflect medical precision, patient autonomy, and cultural sensitivity. Below is a comparative table outlining key terms, their definitions, and associated procedures:
| Term | Definition | Primary Goals | Common Procedures |
|---|---|---|---|
| Sex Reassignment Surgery (SRS) | A historical term referring to surgical interventions to alter primary or secondary sexual characteristics to match gender identity. Often associated with early medical models that framed gender as a "disorder." | Physical alignment with gender identity; reduction of gender dysphoria. | Orchiectomy, mastectomy, vaginoplasty, phalloplasty, metoidioplasty. |
| Gender-Affirming Surgery (GAS) | The contemporary, patient-centered term preferred by medical professionals and advocacy groups. Emphasizes affirmation over "reassignment," reflecting a shift toward self-determination and holistic care. | Improvement of mental and physical well-being; affirmation of gender identity. | All SRS procedures + facial feminization/masculinization, chest contouring, voice surgery. |
| Gender Confirmation Surgery (GCS) | A term used in some regions (e.g., parts of Europe) to describe surgeries that "confirm" a person’s gender identity. Less common in the U.S., where "affirming" is preferred. | Legal and physical confirmation of gender identity. | Same as GAS; may include legal documentation updates. |
| Facial Feminization Surgery (FFS) | A subset of GAS focusing on facial and skeletal modifications to achieve more traditionally feminine features. Often sought by transgender women to enhance gender presentation. | Improvement of facial harmony with gender identity; reduction of dysphoria. | Forehead contouring, rhinoplasty, cheek augmentation, jaw reduction, brow lift. |
The preference for "gender-affirming" over "reassignment" underscores a paradigm shift in transgender healthcare: moving away from a medicalized, pathological framework toward one that centers patient agency. This terminology aligns with the WPATH’s 7th Standards of Care, which state: > "Gender-affirming interventions are medically necessary for the treatment of gender dysphoria and should be provided as part of a comprehensive, multidisciplinary approach."
Table of Contents
- Understanding Sex Reassignment Surgery: Core Concepts and Definitions
- Medical and Non-Medical Definitions of SRS
- Historical Evolution of SRS: Milestones and Societal Shifts
- Terminology Comparison: SRS, GAS, GCS, and FFS
- Global Prevalence and Demographic Trends in SRS
- Types of Sex Reassignment Surgery Procedures: A Comprehensive Breakdown
- Categorization of SRS Procedures by Anatomical Focus
- Comparison of Top 5 Most Common SRS Procedures
- The SRS Process: Step-by-Step Journey from Consultation to Recovery
- Pre-Operative Evaluation Process
- Essential Preparations for SRS Patients
- Hospitalization and Surgical Day
Global Prevalence and Demographic Trends in SRS
Estimating the global prevalence of gender-affirming surgery is challenging due to underreporting, legal restrictions, and cultural stigma. However, available data provides insights into demographic patterns, geographic disparities, and access barriers. Age and Gender Identity:
Geographic Distribution:
Types of Sex Reassignment Surgery Procedures: A Comprehensive Breakdown
Sex reassignment surgery (SRS), also referred to as gender-affirming surgery, encompasses a diverse range of procedures designed to align a person’s physical characteristics with their gender identity. These surgeries target anatomical, functional, and aesthetic aspects, including genital, chest, facial, and vocal modifications. Advances in medical technology and surgical techniques have expanded the possibilities, allowing for highly personalized outcomes. The procedures vary in complexity, recovery duration, and specialization, requiring careful consideration of individual goals, health status, and long-term expectations. Below is a detailed categorization of SRS procedures, structured by anatomical focus, alongside comparative insights, procedural breakdowns, customization options, and emerging trends.
Categorization of SRS Procedures by Anatomical Focus
SRS procedures are broadly grouped based on the anatomical regions they address. Each category serves distinct purposes, ranging from functional improvements to cosmetic enhancements. The following classifications provide a framework for understanding the scope of available options:
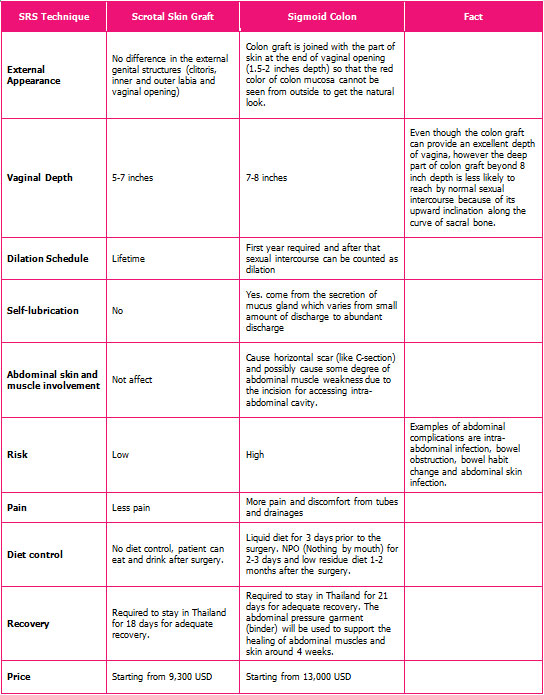
Procedures targeting genital reconstruction, including vaginoplasty, phalloplasty, metoidioplasty, and orchiectomy/hysterectomy. These surgeries address both physical and functional aspects, such as sexual function, urination, and fertility considerations.
Focused on modifying chest anatomy to align with gender identity, including mastectomy (for trans masculine individuals) and breast augmentation (for trans feminine individuals). These procedures also address surgical site sensation and aesthetic symmetry.
Includes procedures like rhinoplasty (nose reshaping), forehead contouring, and chin augmentation to achieve more gender-congruent facial features. These surgeries often complement broader gender-affirming transitions.
Less common but impactful, these procedures may involve vocal cord adjustments or laryngoplasty to modify pitch and vocal characteristics.
Includes hair removal techniques (e.g., laser hair removal for facial/body hair), skin grafting for scar revision, and emerging technologies like 3D-printed implants for genital reconstruction.
Comparison of Top 5 Most Common SRS Procedures
The following table summarizes the five most frequently performed SRS procedures, providing a comparative overview of their purposes, recovery timelines, success rates, risks, and cost estimates. Data for success rates and complications are derived from studies published in The Journal of Sexual Medicine, Plastic and Reconstructive Surgery, and clinical reports from leading gender clinics.
| Procedure Name | Primary Purpose | Recovery Time | Success Rates | Potential Risks/Complications | Cost Estimates (Global Averages) |
|---|---|---|---|---|---|
| Vaginoplasty | Creation of a neovagina from penile and scrotal tissue (penile inversion vaginoplasty) or intestinal tissue (colovaginoplasty). May include clitoral reconstruction. |
|
|
|
$15,000–$30,000 USD (varies by region and technique) |
| Phalloplasty | Construction of a neophallus using radial forearm, anterolateral thigh, or other donor tissue flaps. Often includes urethral lengthening and scrotum creation. |
|
|
|
$50,000–$100,000+ USD (most expensive SRS procedure) |
| Metoidioplasty | Release of the enlarged clitoris (metoid) to create a small phallus, often paired with urethral lengthening and scrotoplasty. Less invasive than phalloplasty. |
|
|
|
$10,000–$25,000 USD |
| Mastectomy (Chest Reconstruction) | Removal of breast tissue and nipple/areola complex for trans masculine individuals. May include nipple-sparing techniques or free nipple grafting. |
|
|
|
$5,000–$15,000 USD |
| Breast Augmentation | Creation or enhancement of breast tissue for trans feminine individuals using implants or fat transfer. May include areola/nipple reconstruction. |
|
|
Essential Preparations for SRS PatientsPreparing for SRS extends beyond medical evaluations to encompass practical, financial, and lifestyle adjustments. A well-structured plan reduces stress, mitigates risks, and ensures a smoother recovery. Below is a checklist of critical preparations, categorized by priority areas. Financial Planning Financial considerations are often a significant stressor for SRS candidates. Costs can range from $10,000 to $50,000+ USD, depending on the procedure, location, and whether insurance covers part or all of the surgery. Key steps include:Hospitalization and Surgical DayThe day of surgery marks the culmination of months of preparation, and understanding the process can alleviate anxiety. Hospitalization duration varies by procedure type, but most patients spend 1–5 days in the facility. Below is a detailed breakdown of what to expect. Anesthesia Types SRS procedures require anesthesia to ensure patient comfort and surgical precision. The choice depends on the surgery’s complexity and surgeon preference:Sex Reassignment Surgery stands at the intersection of medical innovation, personal autonomy, and societal progress, offering transgender individuals a path to bodily integrity and self-acceptance. While challenges remain—from accessing specialized care to navigating recovery—advancements in surgical techniques and supportive therapies continue to improve outcomes. For those considering this journey, understanding the process, from initial consultations to long-term adjustments, is essential. The goal is not just physical transformation but holistic well-being, proving that in the pursuit of gender affirmation, every step forward is a victory for both medicine and human dignity. |
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Holo.